

OTC Collections
Revenue Cycle Transformation
- Capability status
- To be confirmed with PRN
- Transformation phase
- To be confirmed with PRN
- Effort
- To be confirmed with PRN
Current State / What We Learned
Observed today, as captured in the corrected assessment.
This is a metric that front desk teams are doing well at collecting the amounts identified during the initial verification of benefits.
Desired Future State
The target way of working PRN and Raintree are aiming for.
In the future the ideal would be to have feedback mechanisms that assist in updating the amounts to be collected during the course of the patient’s care.
Requirement / Gap
Currently there are not feedback mechanisms that are in use to update amounts to be collected at time of visit that are widely in use.
Raintree Recommended Path
- For this I would suggest a follow up working session on PPAC templates to setup a few samples, which can be set to use the payment terms only while the deductible is not met, or to estimate when then deductible will be met, to more closely align with what the patient owes after insurance adjudication. As noted with the section on refunds these common use cases for a PPAC can be set as a templated model for the teams to work from.
- Another feedback mechanism that is helpful to use as an indication that amounts to collect should be updated are decreasing copay follow up notes within the Follow Up Dashboard. Sorting by this follow up code and then by reason codes can help to give an indication when deductible and/or out of pocket maximums have been met and time of visit collections are no longer needed.
- An additional avenue to consider is that PPAC’s can be sent to patients for signature via the patient portal prior to the first visit. If the patient has the opportunity to review the details in a more focused environment if they do have an HSA that will issue payments to cover their responsibility amount this can provide them more time to share this feedback with the team to ensure that the front desk team does not collect in scenarios where the patient would have payments sent from the HSA with the payor directly following payor adjudication.
Dependencies / Considerations
The suggested workflow would want to have a regional “owner” who could help to define templates for PPAC within their location category, as well as define routing rule within the follow up routing for who would work decrease copay (DECOP) follow up notes.
Outstanding Questions / Decisions
PRN collects roughly 99% OTC of what is due at time of service. The challenges come into play when sometimes the team accidentally over collect and then end up possibly owing the patient, or the patient may pay as prompted at time of service, but then the HSA will send money. Christina mentioned she spoke to Ben about this. They reviewed an example where the team was collecting $70 per visit until patient hits their deductible, then patient meets deductible, the claim adjudicates and no longer does the patient owe. The team see challenges in this type of a scenario because of first in and first out method, the front office and patient are not easily able to indicate that the patient actually is owed $30 back from their first visit. Overall, front desk does a great job collecting, but they need help with getting it more exact to avoid patient over paying.
Evidence
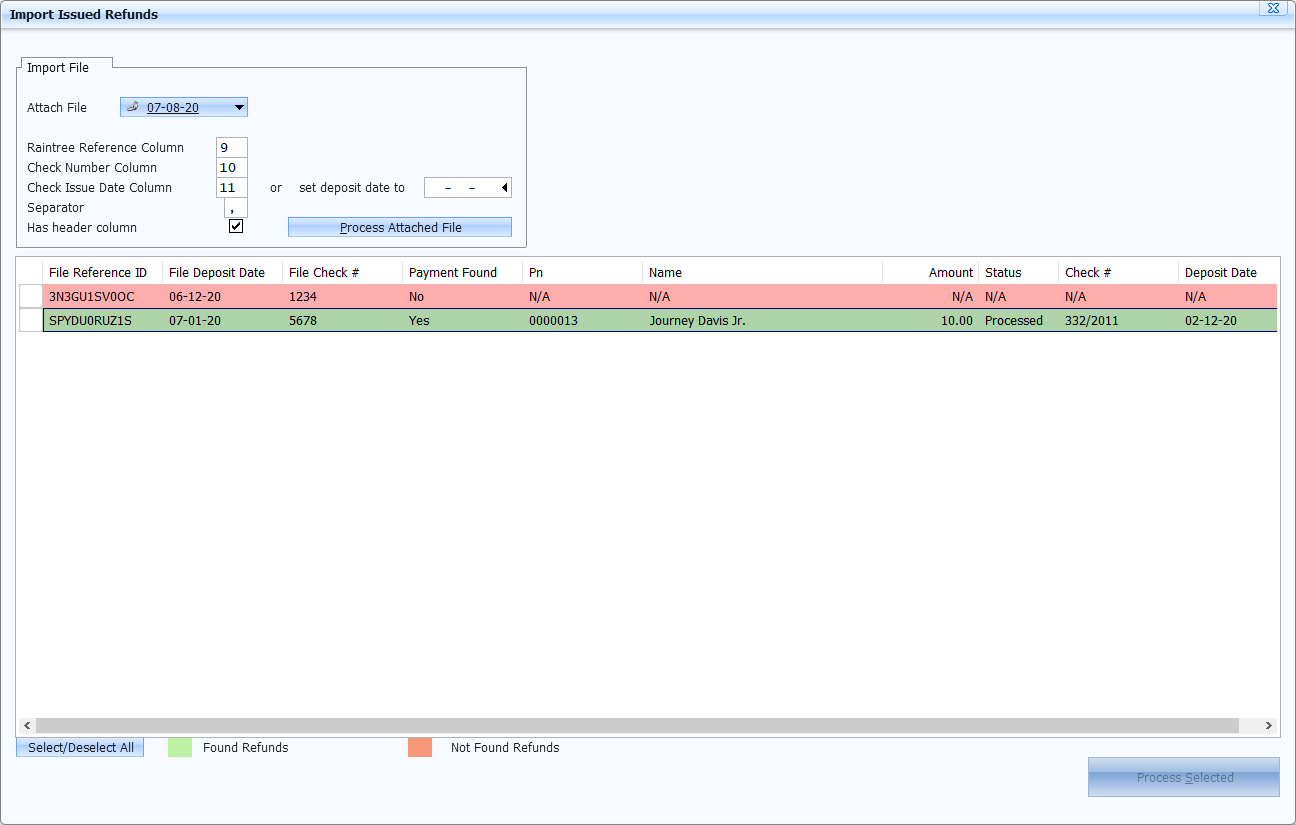
Supporting screenshots from the corrected Detailed Transformation Assessment.
Source
Detailed Transformation Assessment (Corrected)Related opportunities
Related by workstream and subject matter. These are not stated dependencies unless the assessment says so.